When Telehealth for Seniors Works, and When Your Parent Needs the Exam Room
Your mother's cardiologist sits twenty minutes away in traffic that never cooperates. The parking deck is a hike. The appointment itself runs twelve minutes, and eight of those are a blood pressure recheck and a refill. Families do that math constantly, and it is the reason the screen keeps winning.
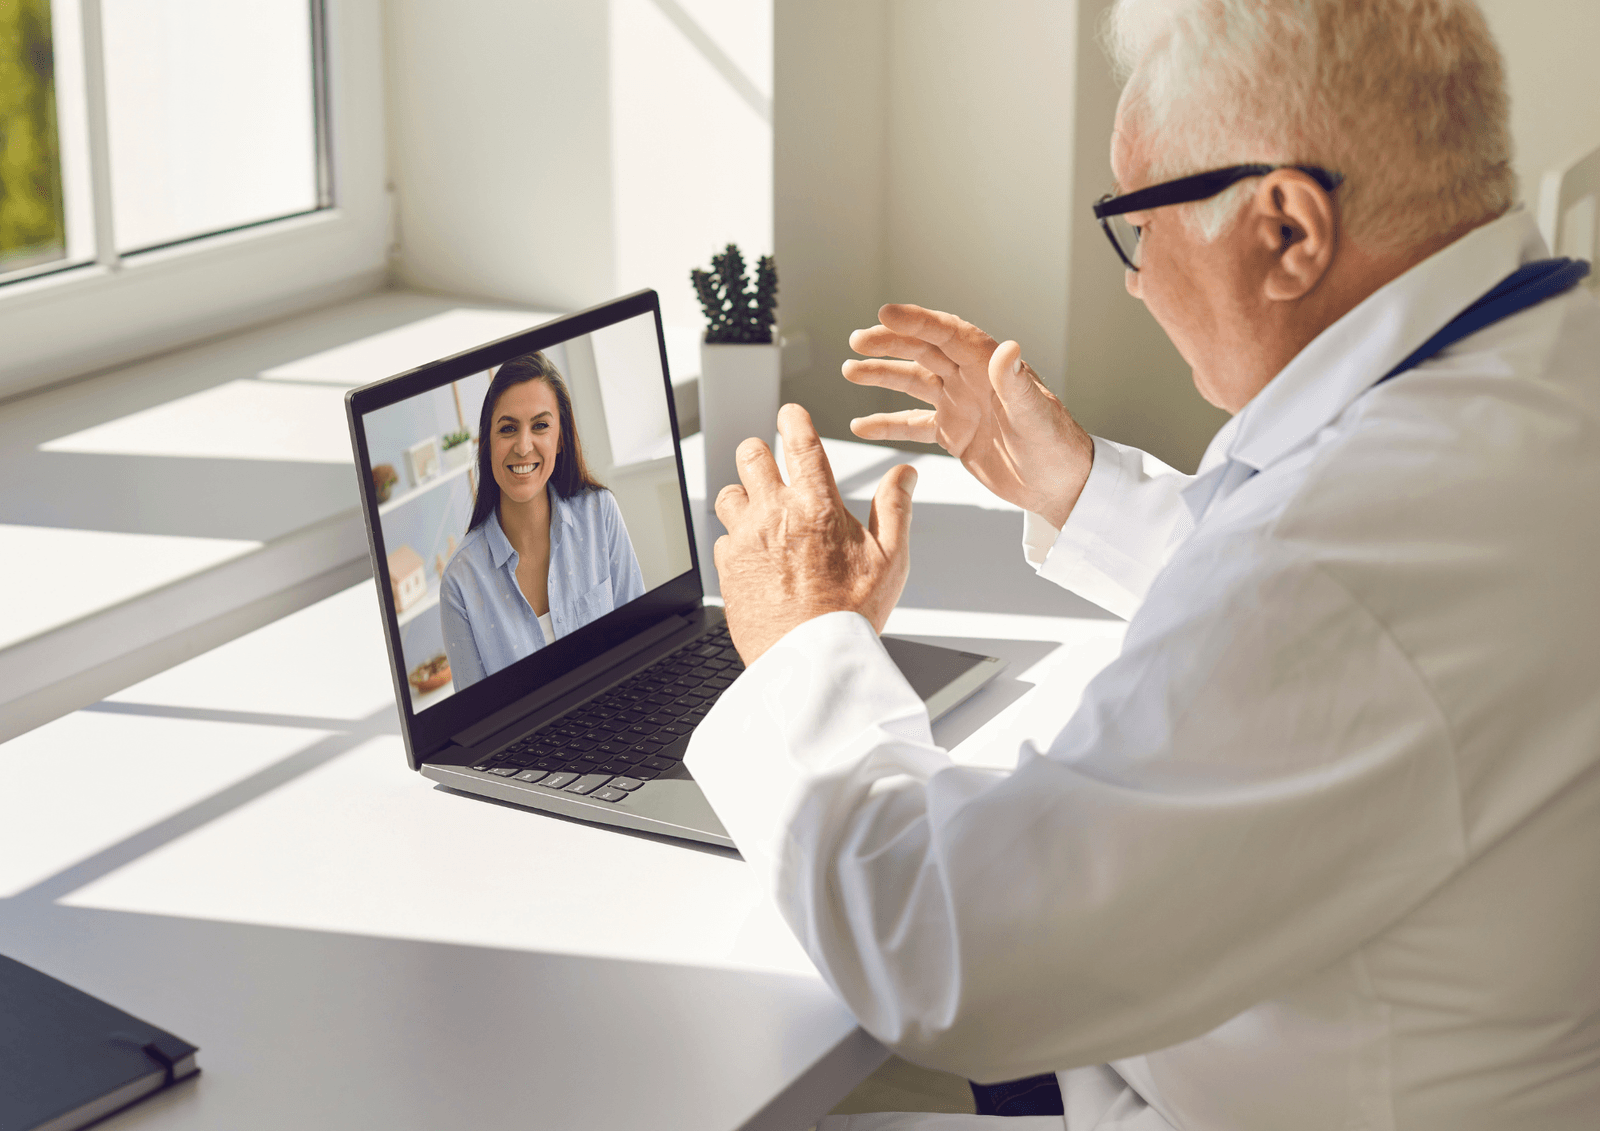
Here is the plain answer. Telehealth for seniors means medical care delivered by video call, phone call, or secure message instead of an office visit. It works well for medication reviews, follow-ups on conditions a doctor already knows about, and mental health care. It does not replace hands-on exams, lab work, imaging, or anything a clinician needs to touch to understand. Used correctly, it is one lane in a care plan. It is not the road. The National Institute on Aging draws the same line, and so does most of what follows. Families already navigating senior assisted living decisions usually find this is the first piece of the puzzle that clicks.
What Telehealth for Seniors Actually Does Well
Not every appointment needs a body in a chair. Three categories translate cleanly to a screen.
Telehealth medication management
This is the strongest use case. A prescriber can review the full list, ask how a new dose is landing, check for duplicated pills across three specialists, and adjust. No driving. No waiting room. For a parent on eight medications, a fifteen-minute video call every few months catches problems that would otherwise wait for the next annual.
One practical detail: have the actual bottles on the table. Not a list. Bottles. Prescribers catch expired dates, wrong pharmacies, and forgotten refills that way.
Follow-ups on conditions the doctor already knows
Blood pressure trends. Diabetes check-ins. A post-surgical incision the surgeon wants to eyeball. Chronic conditions produce a steady drumbeat of short appointments, and most of those are conversations. Federal guidance on behavioral health care and chronic disease management for older adults treats these as core telehealth territory, not edge cases.
Mental health care
This is where the format may actually beat the office. Therapy and psychiatric care require conversation, not palpation. Transportation is often the barrier that keeps an older adult out of treatment entirely, and a video call removes it. Coverage reflects this. A parent without a working camera is not shut out, because federal guidance treats an audio-only visit as a legitimate option when video will not work.
Worth naming plainly: a parent who has become withdrawn, stopped calling, or lost interest in things they used to organize their week around deserves an evaluation. Those are patterns, not diagnoses. A clinician decides what they mean. A video visit is a low-friction way to get that conversation started, and it is far easier to arrange than a first in-person psychiatric appointment. If a parent has named someone to speak on their behalf, a power of attorney makes joining that call and following up considerably simpler.
What Still Requires an In-Person Visit
The limits of telehealth for seniors are not subtle, and pretending otherwise costs families time.
A screen cannot perform a physical exam. No abdominal palpation, no joint assessment, no listening to lungs, no checking for swelling in the ankles. It cannot draw blood, run a urinalysis, take an X-ray, or do an EKG.
Certain situations should route straight to an office or an emergency department:
- Chest pain, shortness of breath, sudden weakness, facial droop, or confusion that came on fast
- A fall, especially one with a head strike or any anticoagulant in the medication list
- A wound that is not healing, or any skin change that needs to be measured and touched
- New pain that has no obvious explanation
- Unexplained weight loss, which almost always requires labs and a scale in a clinic
There is a middle category, too. Remote patient monitoring uses home devices, such as blood pressure cuffs or glucose meters, to send readings to a care team between appointments. That is not a substitute for an exam. It is a tripwire. It tells a clinician when to bring your parent in sooner.
The honest framing: telehealth is excellent at maintaining care and poor at discovering what is wrong for the first time.
How Does Telehealth Work for a Parent Who Has Never Video Called Anyone?
The technology is the part families underestimate. Research backs that up. In a study published in JAMA Internal Medicine, Kenneth Lam, Amy Lu, Ying Shi, and Kenneth Covinsky of the University of California, San Francisco found that roughly 38% of adults over 65 were unready for video visits, owing to hearing or vision difficulty, communication problems, or inexperience with the devices themselves. Among adults 85 and older, that figure reached 72%.
A later mixed-methods study in JMIR Aging, conducted at two independent living facilities, found the same thing from the resident's side. The dominant complaint was not skepticism about virtual care. It was that learning the technology felt overwhelming, and that people wanted hands-on help rather than a PDF.
So with telehealth for seniors, the setup work matters more than the call itself.
Do this before the first appointment:
- Pick one device and stop switching. A tablet is usually easier than a phone. Bigger screen, easier to prop up.
- Log into the patient portal together and write the password down on paper. Keep it somewhere your parent can find it without calling you.
- Do a practice call the day before. Same device, same room, same chair. Video call your parent for ten minutes about nothing.
- Check the light. A window behind your parent turns them into a silhouette. Move the chair so the light hits their face.
- Sort out the audio. Hearing loss plus tinny tablet speakers is a bad combination. Headphones or a Bluetooth speaker fixes most of it.
- Log on fifteen minutes early. Technical problems before the appointment are annoying. Technical problems during it eat the appointment.
Ask the practice whether a staff member will do a test run. Many will. Federal guidance actively recommends it, and offices that serve a lot of older patients often have someone whose job includes exactly that. It is a reasonable thing to request, the same way our care team fields these questions from families every week.
Does Medicare Cover Telehealth Right Now?
Yes, and the current rules are broader than most families assume.
The Consolidated Appropriations Act, 2026, signed in February 2026, extended Medicare's pandemic-era telehealth flexibilities through December 31, 2027. That means no geographic restriction and no requirement that your parent travel to a qualifying facility. They can take the visit from their own living room. The current Medicare telehealth rules also keep audio-only options open for patients who cannot manage video, and audio-only behavioral health services sit on permanent footing.
Cost-wise, telehealth under Part B works like any other outpatient visit. After the Part B deductible, your parent is generally responsible for 20% of the Medicare-approved amount. Medicare Advantage plans must cover at least what Original Medicare does, and many offer more, so check the specific plan rather than assuming.
Two cautions. First, these flexibilities are extensions, not permanent law, and they have lapsed briefly before. Second, coverage is not the same question as eligibility for long-term care, which trips up a lot of families. Medicare and assisted living are governed by entirely different rules than Medicare and a video appointment.
Where Telehealth Belongs in the Whole Care Plan
Consider a pattern that repeats across Richmond's West End.
An adult daughter notices her father is repeating himself on the phone and seems foggier than he did a month ago. She books a video visit, which she gets in three days instead of three weeks. During the call, the physician asks about recent falls, reviews his medication list, and watches him walk across the room. She does not diagnose anything. She says the change is significant enough to need labs and a hands-on exam, and she orders both for that week.
The video call did not solve the problem. It compressed the timeline from weeks to days, and it did so because someone was sitting next to him, working the tablet and filling in details he had already forgotten. That is the actual pattern. Telehealth for seniors performs in direct proportion to the support standing beside it.
Which is the part families tend to discover late. A screen does not notice that dinner went uneaten three nights running. It does not see that your mother stopped going downstairs. It cannot tell you she has been wearing the same cardigan for a week. In a memory care setting, or any setting with staff who see a resident daily, those observations become the raw material a telehealth visit runs on. Without them, the clinician is working from whatever your parent chooses to report.
Build the plan so the two support each other. Use virtual visits for medication reviews, mental health, and routine follow-up. Protect in-person appointments for annual exams, anything new, and anything physical. Keep one current medication list that everyone works from, and prepare for the visit with written questions, because twelve minutes disappears fast either way.
Telehealth for seniors carries more than most families expect and less than the marketing suggests. It cannot notice what nobody reports. Someone has to be in the room.
Tell our Short Pump team what a typical week actually looks like at home right now, including the appointments that keep slipping and the ones nobody wants to drive to. We will be straight with you about which parts of your parent's care a screen can genuinely carry, and which parts need a person standing there.
Sources:
- https://www.nia.nih.gov/health/medical-care-and-appointments/telehealth-what-it-how-prepare-it-covered
- https://telehealth.hhs.gov/providers/best-practice-guides/telehealth-older-adults/getting-started
- https://www.cms.gov/files/document/telehealth-faq-updated-02-26-2026.pdf
- https://jamanetwork.com/journals/jamainternalmedicine/fullarticle/2768772
- https://medlineplus.gov/telehealth.html
- https://aging.jmir.org/2022/2/e34326
- https://telehealth.hhs.gov/patients/what-should-i-know-before-my-telehealth-visit
- https://telehealth.hhs.gov/providers/best-practice-guides/telehealth-older-adults/preparing-older-adults-telehealth
Frequently Asked Questions
Does Medicare cover telehealth?
Yes. Original Medicare covers telehealth under Part B, and current flexibilities allowing home-based visits run through December 31, 2027.
What is a telehealth appointment?
It is a medical visit conducted by live video, phone call, or secure messaging rather than in an office. The clinician and patient are in different locations.
Is telehealth for seniors as effective as an in-person visit?
For medication reviews, mental health care, and follow-up on known conditions, it performs comparably. For anything requiring a physical exam, lab work, or imaging, it does not substitute.
How do telehealth appointments work?
Your parent logs into the provider's portal or app at the appointment time, and the clinician joins the call. A caregiver may sit in and help with the device.
Can a telehealth doctor prescribe antibiotics?
Often yes, for straightforward conditions the prescriber can assess by conversation and history. Prescribing rules vary by state and by drug class, particularly for controlled substances.
What are the important differences between telehealth and in-person care?
Telehealth removes travel and shortens wait times but cannot include physical examination, blood draws, or imaging. In-person care covers everything telehealth does plus hands-on assessment.